Control of blood water potential
Studying this course? Keep your progress in one place.
Key facts
- Osmoreceptors in the hypothalamus detect blood water potential; ADH is made there and released from the posterior pituitary.
- Ultrafiltration in the glomerulus is by pressure and size: glucose is filtered but later reabsorbed in the PCT.
- The loop of Henle builds a sodium ion gradient in the medulla.
- ADH inserts aquaporins in the DCT and collecting duct: more ADH means less, more concentrated urine.
Osmoregulation and ADH
Osmoreceptors in the hypothalamus detect changes in blood water potential. ADH is made in the hypothalamus and released from the posterior pituitary.
Osmoregulation is the control of blood water potential. It matters because blood water potential sets that of tissue fluid and so the water content of cells.
Osmoreceptors in the hypothalamus detect a fall (after sweating or a salty meal) or a rise (after drinking). Neurosecretory cells there make antidiuretic hormone (ADH) and pass it along their axons to the posterior pituitary gland, where it is stored and released into capillaries when needed.
- 1
Osmoreceptors
in the hypothalamus detect the change in blood water potential
- 2
Neurosecretory cells
in the hypothalamus make ADH
- 3
Axons carry ADH
to the posterior pituitary gland, where it is stored
- 4
Release into the blood
capillaries when needed
Where is ADH stored and released into the blood?
The nephron and ultrafiltration
High hydrostatic pressure in the glomerulus forces small molecules out through three layers into the Bowman’s capsule, while large proteins stay in the blood.
Each kidney has about a million nephrons. The cortex holds the Bowman's capsule, glomerulus and tubules; the medulla holds the loop of Henle and collecting duct.
The afferent arteriole is wider than the efferent arteriole, so hydrostatic pressure in the glomerulus is high. It forces water, glucose, urea and ions out through the capillary endothelium, the basement membrane and the podocytes. The fluid is the glomerular filtrate.
- 1
Wide afferent arteriole
brings blood into the glomerulus
- 2
Narrow efferent arteriole
so the hydrostatic pressure is high
- 3
Endothelium
capillary wall with gaps
- 4
Basement membrane
holds back large molecules such as plasma proteins
- 5
Podocytes
of the Bowman’s capsule; the filtrate enters the capsule
Why is the hydrostatic pressure in the glomerulus high?
Reabsorption in the PCT
The PCT reabsorbs all the glucose and most of the water and ions, using active transport of sodium ions and co-transport of glucose.
The proximal convoluted tubule (PCT) cells have microvilli and many mitochondria.
- Sodium ions are actively transported out of the cells into the blood.
- Sodium ions enter from the filtrate by facilitated diffusion, and glucose enters with them by co-transport.
- Glucose passes into the blood by facilitated diffusion.
Water follows by osmosis. If the filtrate holds more glucose than the carriers can take up, some stays in the urine.
- 1
Active transport
moves sodium ions out of the cell into the blood
- 2
Sodium ions enter
from the filtrate by facilitated diffusion
- 3
Co-transport
brings glucose into the cell with the sodium ions
- 4
Facilitated diffusion
moves glucose into the blood
Why might glucose appear in the urine?
The loop of Henle
The ascending limb pumps sodium ions into the medulla, giving it a low water potential, so water leaves the descending limb by osmosis.
The loop of Henle creates a gradient of sodium ions in the medulla. The ascending limb is impermeable to water, so water stays in the tubule while sodium ions are pumped out. This gives the medulla a low water potential, lowest deep in the medulla.
The descending limb is permeable to water, so water leaves it by osmosis and the filtrate becomes more concentrated.
Animals with longer loops of Henle, such as desert mammals, build a steeper gradient and make more concentrated urine.
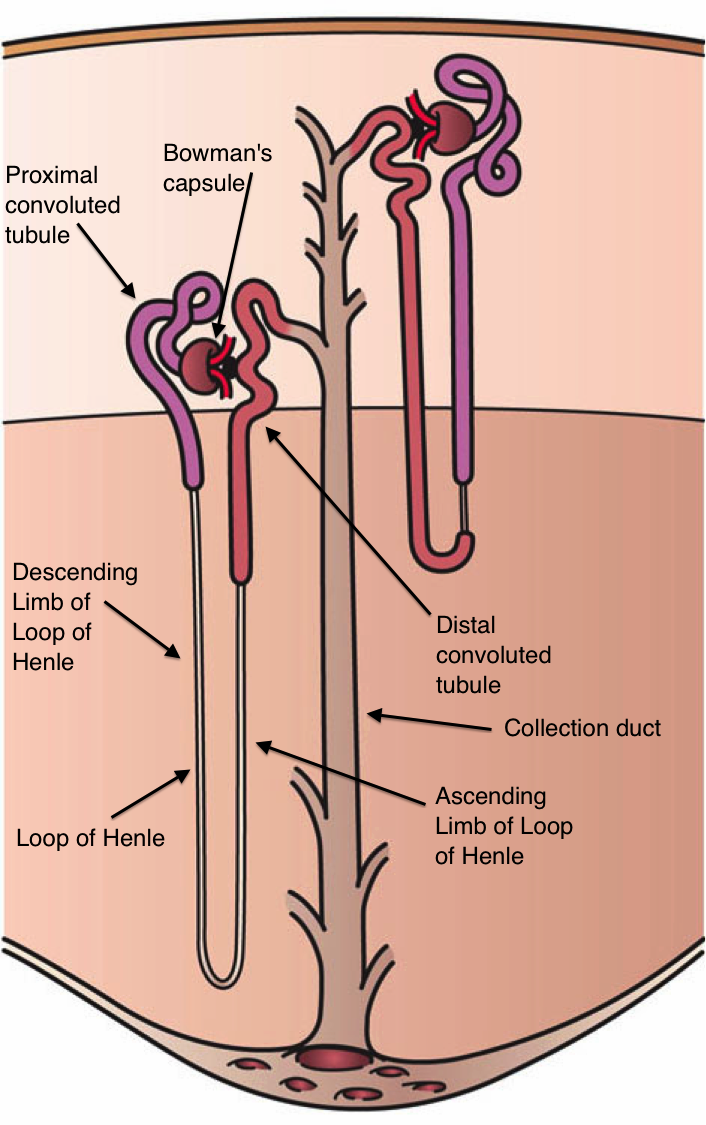
| Ascending limb | Descending limb | |
|---|---|---|
| Water | Impermeable to water | Permeable to water |
| What happens | Sodium ions actively transported out into the medulla | Water leaves by osmosis; filtrate becomes more concentrated |
Ascending limb
- Water:
- Impermeable to water
- What happens:
- Sodium ions actively transported out into the medulla
Descending limb
- Water:
- Permeable to water
- What happens:
- Water leaves by osmosis; filtrate becomes more concentrated
Why do desert mammals make very concentrated urine?
The DCT and collecting duct
ADH makes the DCT and collecting duct more permeable to water by inserting aquaporins, so more water is reabsorbed into the low-water-potential medulla.
Filtrate in the distal convoluted tubule (DCT) and collecting duct passes through the medulla, where tissue fluid has a low water potential. Water can leave by osmosis only if the walls are permeable, and this is controlled by ADH.
ADH binds to receptors on the cell surface membranes, leading to more aquaporins being inserted. More water is reabsorbed, giving a small volume of concentrated urine. With no ADH the walls stay impermeable and a large volume of dilute urine is made.
- 1
Blood water potential falls
ADH is released into the blood
- 2
ADH binds to receptors
on the collecting duct cell surface membranes
- 3
More aquaporins inserted
walls become permeable to water
- 4
More water reabsorbed by osmosis
into the low-water-potential medulla
- 5
Small volume of concentrated urine
| ADH present | No ADH | |
|---|---|---|
| Aquaporins | More inserted | Not inserted |
| Wall permeability to water | Permeable | Impermeable |
| Urine | Small volume, concentrated | Large volume, dilute |
ADH present
- Aquaporins:
- More inserted
- Wall permeability to water:
- Permeable
- Urine:
- Small volume, concentrated
No ADH
- Aquaporins:
- Not inserted
- Wall permeability to water:
- Impermeable
- Urine:
- Large volume, dilute
How does ADH make the collecting duct more permeable to water?
The full feedback loop
A fall in blood water potential releases more ADH, giving concentrated urine; a rise releases less ADH, giving dilute urine. Both are negative feedback.
Blood water potential falls: osmoreceptors detect it, the hypothalamus stimulates the posterior pituitary to release more ADH, the DCT and collecting ducts become more permeable, more water is reabsorbed and the water potential rises.
Blood water potential rises: less ADH is released, the walls stay less permeable, more dilute urine is produced and the water potential falls back to normal.
The hypothalamus also triggers thirst.
- 1
Water potential falls
detected by osmoreceptors in the hypothalamus
- 2
More ADH released
from the posterior pituitary
- 3
DCT and collecting ducts more permeable
more aquaporins
- 4
More water reabsorbed
small volume of concentrated urine
- 5
Water potential rises
back towards normal
Then back to step 1
Blood water potential rises after drinking a lot. What happens to ADH release and urine?
Try an exam question
A person sweats heavily on a hot day. Explain how the kidneys respond to restore the water potential of the blood.
[5 marks]
- [1]Blood water potential falls and osmoreceptors in the hypothalamus detect the change.
- [1]The posterior pituitary releases more ADH into the blood.
- [1]ADH binds to receptors on the DCT and collecting duct cells, so more aquaporins are inserted.
- [1]The walls become more permeable, so more water is reabsorbed by osmosis from the filtrate.
- [1]A small volume of concentrated urine is produced and blood water potential rises.
That's the notes covered.
Carry on to the next subtopic.
Try a question
Which structure detects the fall in the water potential of the runner's blood?
1 mark, marked against the mark scheme
Which structure detects the fall in the water potential of the runner's blood?
1 mark, marked against the mark scheme